
Almost every day, someone asks me which vagus nerve stimulator I recommend. It is a reasonable question, and with so many products and claims to sort through, answering it responsibly has become increasingly difficult.
Vagal tone has become a familiar topic in trauma treatment, psychotherapy, and everyday conversations about health. Devices designed to stimulate the vagus nerve are marketed directly to us, while breathwork, cold exposure, movement, sound, and other practices I recommend and believe in are routinely described as ways to “tone,” “reset,” or regulate it. Polyvagal language now appears throughout psychotherapy, coaching, wellness culture, and social media.
I welcome the growing recognition of how deeply trauma affects our bodies: how we sleep and digest, how we experience emotion and connect with others, and how readily we move between activity and rest. This attention has helped broaden our understanding of mental health through a trauma lens. As interest grows, though, I find myself looking more closely at the claims being made and whether the research supports what we are being encouraged to buy or practice.
How I approach autonomic regulation
I have been working with these questions for many years. In Rhythms of Recovery, published in 2013 and updated in 2023, I explored the autonomic nervous system and methods of self-regulation as part of trauma treatment. My approach brings this physiology into conversation with Ayurvedic and Chinese medicine, botanical medicine, and nutrition. I am interested in how we breathe, eat, move, sleep, and relate to our surroundings, and how attending to these everyday experiences can become part of recovery.
Traditional healing systems have their own ways of understanding bodily rhythms. I approach them on their own terms while considering what contemporary research can help us understand. Describing all of these practices as vagus nerve stimulation would leave out much of what they involve, including the relationships, environments, and cultural meanings that shape our experience of them.
Trauma and autonomic regulation involve multiple systems, and treatment needs to take that complexity into account. This is why I become cautious when “the vagus nerve” is offered as the explanation for anxiety, dissociation, digestive symptoms, sleep disturbance, social withdrawal, emotional reactivity, resilience, and trauma recovery all at once. A single pathway can be clinically important without becoming a master explanation. When one piece of the jigsaw is asked to explain the whole picture, we lose precision rather than gain it.
Reading the research behind the claims
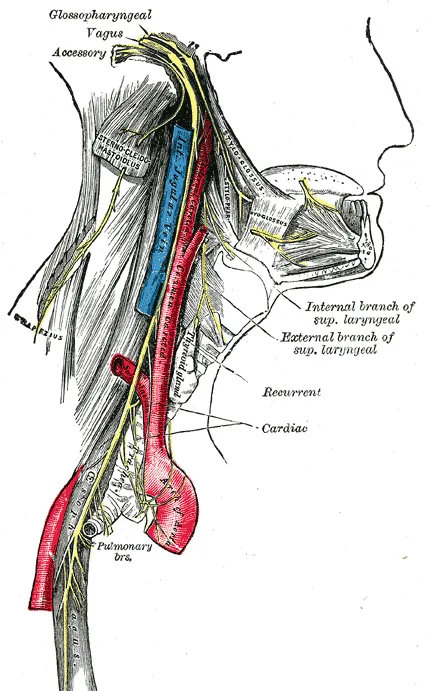
Research on vagus nerve stimulation, or VNS, is not automatically evidence for every commercial device described as a “vagus nerve stimulator.” Different studies may use different technologies, anatomical targets, stimulation parameters, treatment schedules, and patient populations.
So the clinically meaningful question goes beyond “Does vagus nerve stimulation work?” We need to ask which form of stimulation, delivered how, for which condition, in which population, and with what outcome. These details matter when interpreting the results and applying them in clinical practice.
What Does the Evidence Say About Trauma?
A 2025 systematic review by Benzouak and colleagues examined transcutaneous vagal nerve stimulation for trauma- and stressor-related disorders. The authors identified 322 abstracts and ultimately included seven randomized controlled studies. Their conclusion was appropriately cautious: the evidence for VNS as a treatment intervention for trauma- and stressor-related disorders, particularly PTSD, was limited, and the overall certainty of evidence was rated very low.
That does not mean that no effects were observed or that individual participants experienced no benefit. Systematic reviews bring together findings from multiple studies, and what works for one person may not work for another. The review found evidence suggesting that VNS may alter specific aspects of PTSD, including reductions in anger responses and attenuation of hyperarousal during psychological interventions. To understand how these findings apply in practice, I always check which product was used, whether the research concerns a device, a nutritional supplement, or an herb. I want to know whether the product being recommended is the same one that was actually studied.
A second 2025 study offers interesting findings. Powers, Hays, Rosenfield, and colleagues examined vagus nerve stimulation paired with prolonged exposure therapy in nine people with treatment-resistant PTSD. The reported results were substantial. Participants demonstrated significant and clinically meaningful improvements across several measures of symptoms and severity, including the CAPS-5, PCL-5, and HADS, with all reported at p < 0.001 following treatment.
The benefits persisted six months after therapy ended, and all participants no longer met criteria for a PTSD diagnosis after completing treatment. No serious or unexpected device-related adverse events were reported. This was a small, open-label feasibility study without a control group, so it could not determine how much benefit VNS added to psychotherapy. The authors presented it as an initial step toward more rigorous randomized controlled studies.
Polyvagal Theory: Clinical Usefulness and Scientific Debate
We also need to distinguish VNS research from Polyvagal Theory. The two conversations overlap, but they are not interchangeable. In his 2025 review, Stephen Porges examines Polyvagal Theory, its clinical applications, and future directions. The theory proposes an evolutionarily informed neurophysiological framework for understanding how the autonomic nervous system participates in social engagement, emotional resilience, and adaptive physiological responses. It emphasizes a hierarchical organization of autonomic states and gives particular attention to vagal pathways involved in social behavior and physiological flexibility. The review also addresses methodological critiques, particularly questions concerning anatomical specificity and the interpretation of respiratory sinus arrhythmia, or RSA.
A theory can inform clinical practice even while some of its components remain unsettled. Indeed we often treat using clinical methods for years before there is any scientific investigation. Concepts such as co-regulation, physiological flexibility, social engagement, and the importance of perceived safety have influenced how many clinicians understand the embodied dimensions of trauma. But clinical usefulness should not quietly become biological certainty. We should be able to use a framework without turning it into dogma and remain willing to revise it as the science evolves.
Working with the Body’s Rhythms
One reason I resist reducing autonomic regulation to a device is that human beings have long developed ways to influence physiological state. Ayurvedic and Chinese medical traditions, botanical medicine, nutritional medicine, and other traditional healing systems have attended to rhythms of food, breath, digestion, movement, rest, temperature, sleep, sensory experience, season, and environment. Their languages differ from those of contemporary neuroscience, but their close observation of bodily rhythm remains relevant.
When we eat and how we breathe, move, and digest all matter. Autonomic self-regulation did not begin with an electrode, a wearable, or a smartphone app. Modern neuroscience has much to teach us, alongside observations developed through generations of traditional healing and clinical practice. My work draws on traditional healing practices as well as contemporary research. With breathing, temperature, and movement increasingly described as ways to stimulate the vagus nerve, I want to look more closely at what these practices do and how we explain their effects.
Breath, Cold Exposure, and Movement
Breathing Practices
Breathing practices are frequently described as methods of “stimulating the vagus nerve,” and that language deserves more precision. Breathing can change physiological state: altering respiratory rhythm can influence cardiovascular rhythms, attention, bodily sensation, and subjective experience. But saying a breathing practice influences autonomic regulation is different from saying it therapeutically stimulates the vagus nerve.
The same caution applies to humming, chanting, singing, gargling, and other practices routinely presented online as “vagus nerve exercises.” Some people find these practices calming or organizing. Some practices may alter respiratory, sensory, or attentional patterns. Some may fit into a larger self-regulation plan. But we should not claim a specific vagal mechanism simply because a practice produces a noticeable bodily effect.
Cold Exposure
Cold exposure is a strong physiological stimulus, and describing it as a way to “calm the vagus nerve” oversimplifies its effects. For some people, carefully chosen temperature changes may feel energizing or become part of a broader sensory practice. For others, abrupt cold exposure can be intensely activating. A powerful physiological response is not necessarily a therapeutic response. Increased activation is not automatically beneficial just because it has been reframed as nervous-system training. The relevant question is not simply whether the intervention produces sensation. It is what that intervention does to this person, in this body, with this history, at this point in treatment. That is “bio-individuality” in practice.
Movement
Movement has long been central to my approach to trauma recovery because regulation is not merely cognitive: we regulate through posture and breath, rhythm and movement, exertion and rest. It may help a person restore a sense of agency and become more aware of activation without becoming overwhelmed, contributing to the process of rebuilding a relationship with a body that has been defended, immobilized, hypervigilant, or numb.
But I resist reducing these effects to a single nerve. Some benefit from aerobic exercise, others from anaerobic activity, and still others from the gentle quiet of Tai Chi, with each approach best adapted to the individual and their stage of recovery.
Regulation Does Not Mean Being Calm All the Time
One of the more troubling simplifications in the current nervous-system conversation is the idea that regulation means being calm all the time. A well-regulated nervous system mobilizes when needed and rests when appropriate. It responds to danger, experiences excitement, moves toward connection, and can withdraw when necessary. Health involves the flexibility to move among these states and recover as our circumstances change.
I think of this as rhythm. Trauma can disrupt that rhythm, and we may become stuck in hyperarousal, collapse, vigilance, numbness, or rapid oscillation between states. The therapeutic task is to restore a greater capacity for modulation, flexibility, and recovery, which involves more than simply turning the nervous system “down.”
What I Consider Before Recommending a Vagus Nerve Stimulator
So, when someone asks me which vagus nerve stimulator I recommend, I begin somewhere else. I want to know what they hope the device will accomplish.
Then I ask:
- What evidence exists for this specific device?
- Was this specific device used in the research being cited?
- What condition was studied?
- Was the stimulation invasive or noninvasive?
- Where was the stimulation delivered?
- What treatment parameters were used?
- Was VNS used alone or paired with psychotherapy or another intervention?
- How large was the study?
- What adverse events occurred?
- How long did benefits persist?
- And does the available evidence justify the claim being made?
- I also consider financial resources. Can you afford it? Is it worth it?
- Could breath, movement, acupuncture, pressure point massage or temperature-based practices help address the same goals?
These questions help distinguish theoretical and biological explanations from demonstrated clinical effectiveness, while taking individual circumstances into account. I explore the art and science of clinical practice with both curiosity and discernment. Thoughtful experimentation can have a place in this work, with attention to potential risks and individual responses. Let’s approach new trends and claims thoughtfully, keeping each client’s needs and responses at the center of our decisions.
References
Benzouak T, Danyluck C, Gunpat S, et al. Transcutaneous vagal nerve stimulation for the treatment of trauma- and stressor-related disorders: systematic review of randomised controlled studies. BJPsych Open. 2025;11(5). doi:10.1192/bjo.2025.10057.
Powers MB, Hays SA, Rosenfield D, et al. Vagus nerve stimulation therapy for treatment-resistant PTSD. Brain Stimulation. 2025;18(3):665–675. doi:10.1016/j.brs.2025.03.007.
Porges SW. Polyvagal Theory: Current Status, Clinical Applications, and Future Directions. Clinical Neuropsychiatry. 2025;22(3):169–184. doi:10.36131/cnfioritieditore20250301.
Clinical note: The approaches discussed here should be adapted to each person’s medical and psychiatric history. Decisions about VNS devices and other therapeutic interventions should be made with an appropriately qualified licensed health professional.

She served as a Fulbright scholar on traditional medicine, a Clinical Fellow at Harvard Medical School, and a National Institutes of Health-funded research scientist in mind/body medicine.
- The Vagus Nerve in Trauma Treatment: Evidence, Exaggeration, and Clinical Judgment - September 16, 2026
- Bioactive Peptides for Stress, Autonomic Regulation, and Sleep - August 17, 2026
- Orthosomnia: When the Pursuit of Perfect Sleep Becomes the Problem - July 6, 2026

Are You Ready to Advance Your Career?
If you want to advance your career in integrative medicine, explore my courses and certifications.